Key Takeaways
- GBS and MS are both autoimmune, demyelinating disorders, but GBS attacks the peripheral nerves, while MS attacks the central nervous system (brain and spinal cord).
- GBS usually comes on fast (days to weeks), often after an infection, and is typically a one-time illness. MS develops gradually and is a lifelong condition.
- Since both damage myelin and cause tingling and weakness, GBS can be mistaken for MS early on, but nerve conduction studies, MRI, and spinal fluid tests help doctors tell them apart.
- Most people with GBS recover substantially within weeks to months; MS requires long-term management to slow progression and reduce relapses.
- IVIG and plasma exchange are mainstays for GBS, while MS is managed with disease-modifying therapies (DMTs) and steroids during relapses.
Get IVIG Copay Assistance
Speak to a SpecialistGuillain-Barre syndrome (GBS) and multiple sclerosis (MS) are both demyelinating autoimmune diseases. Though GBS and MS are autoimmune conditions that damage nerves and have no fully understood cause, they differ in crucial ways; most notably, GBS is usually a temporary, one-time illness, while MS is a lifelong condition.
GBS and MS can be distinguished based on their disease-targeted components, onset and trigger points, signs and symptoms, affected populations, diagnostic tests, treatment approaches, and long-term outlook.
In this guide, we will look closer at the distinctions between Guillain-Barre vs. multiple sclerosis to give you a better understanding of both conditions, starting with a quick side-by-side comparison.
Guillain-Barre Syndrome vs. Multiple Sclerosis: Quick Comparison
The table below breaks down how Guillain-Barre syndrome and multiple sclerosis differ across the factors that matter most: the nerves they affect, their symptoms, how they are diagnosed, and their long-term outlook.
| Feature | Guillain-Barre Syndrome (GBS) | Multiple Sclerosis (MS) |
| Nerves affected | Peripheral nervous system (nerves outside the brain and spinal cord) | Central nervous system (brain and spinal cord) |
| Onset | Rapid – days to weeks, often after an infection | Gradual –symptoms come and go (relapsing) or slowly progress over years |
| Disease course | Usually monophasic (a single episode) | Chronic and lifelong |
| Common triggers | Preceding infection (e.g., Campylobacter jejuni, flu, CMV, EBV, COVID-19) | Genetic + environmental factors (EBV, smoking, low vitamin D) |
| Who it affects | Any age; risk rises with age; affects men and women about equally | Usually ages 20–40; about 3x more common in women |
| Key tests | Lumbar puncture, nerve conduction studies (NCS), EMG | MRI, lumbar puncture (oligoclonal bands), evoked potentials |
| Myelin damage | Often reversible | Usually permanent |
| Prognosis | Most people recover, often within weeks to months | Lifelong management; outlook varies by person |
What GBS and MS Target in the Nervous System
In both MS and GBS, the immune system, which serves as the body’s natural defense against harmful microorganisms like bacteria and viruses, begins to abnormally attack the neurons, which are the communication cells of the nervous system.
In particular, the immune system damages or destroys the protective layer called the myelin sheath that surrounds the axons of the neurons. Myelin sheath primarily helps in rapid signal transmission from the nervous system to the rest of your body’s organs and vice versa.
Damage to the myelin sheath breaks down the communication between the neurons and ultimately leads to progressive loss of all sorts of cognitive, motor, and sensory functions.
Multiple sclerosis and Guillain-Barre syndrome seem similar, but notable differences exist that distinguish both conditions and help healthcare professionals use different treatment approaches accordingly.
Disease-Targeted Components in GBS
In Guillain-Barre syndrome, the immune system destroys the myelin sheath of the peripheral nervous system (a wide array of nerves outside the brain and spinal cord).
The immune response often targets the Schwann cells, which are important for myelin production in these peripheral nerves.
Peripheral nerves allow the brain to communicate with the rest of your body’s organs, like the heart, lungs, kidneys, muscles, etc.
Damage to these nerves disrupts signal transmission, leading to muscle weakness, numbness, or, in most cases, flaccid paralysis and, in severe cases, temporary paralysis. One of the differences between GBS and MS is that the myelin damage in GBS is generally reversible.
Disease-Targeted Components in MS
In contrast, in the case of multiple sclerosis, the immune system damages the myelin sheath of the central nervous system (brain and spinal cord) and the cells producing myelin sheath.
The central nervous system’s myelin damage is often marked by the formation of sclerotic plaques, which disrupt the flow of electrical impulses between the brain and the body.
This process can lead to the progressive degeneration of neurons, which may exacerbate symptoms like cognitive dysfunction, spasticity, and fatigue. Since this nerve damage is often permanent, MS can lead to lasting problems with vision and movement.
Get Your IVIG Dose
At-Home InfusionWho Gets GBS vs. MS? Prevalence and Risk Factors
Understanding the difference between GBS and MS is also crucial for recognizing how they affect different demographics. Let’s explore the prevalence and risk factors associated with each condition.
Risk of GBS
GBS occurs in both males and females equally. But as you age, your risk of developing GBS increases. GBS is rare and affects only about 1 in 100,000 people each year, according to the National Institute of Neurological Disorders and Stroke report – an estimated 3,000 to 6,000 people develop GBS in the United States annually.
Risk of MS
The risk of developing MS is three-fold higher in the female population than in males, with an expected age of onset between 20 and 40 years old. Approximately 2.9 million people have MS worldwide, and nearly 1 million people live with MS in the United States, according to the Atlas of MS and the National Multiple Sclerosis Society.
Can IVIG help?
Free IVIG Treatment InfoWhat Triggers GBS vs. MS?
Although both multiple sclerosis and Guillain-Barre syndrome are neurological autoimmune disorders, they have different trigger points that can initiate symptoms and disease progression.
The Onset and Trigger Points of GBS
The onset of GBS symptoms is mainly preceded by bacterial or viral infections. Some possible triggering causes of Guillain-Barre syndrome include infections with pathogens such as Campylobacter jejuni, Haemophilus influenzae, cytomegalovirus, Epstein-Barr virus, Zika virus, influenza, and SARS-Cov-2.
Other triggers may include certain vaccines, HIV or AIDS, Hodgkin’s disease, or surgery.
The Onset and Trigger Points of MS
A notable difference between GBS and MS is that MS is triggered by environmental factors, which include smoking, vitamin D deficiency, and genetic association.
Although multiple sclerosis is not directly inherited, a person may be more likely to develop MS if they have biological relatives with MS.
In other words, multiple sclerosis has a genetic risk that might be inherited. The heritability of multiple sclerosis has been estimated to be between 35% and 75%.
Furthermore, some viral infections such as Epstein-Barr virus (EBV), measles, and herpes virus-6 can also trigger the onset of multiple sclerosis. These infections cause myelin inflammation.
EBV, in particular, has emerged as a leading risk factor: a large 2022 study published in Science found that infection with EBV dramatically raises the risk of later developing MS, making it one of the strongest known contributors to the disease.
Guillain-Barre Syndrome vs. Multiple Sclerosis: Early Signs and Symptoms

Recognizing the early signs of multiple sclerosis and Guillain-Barre syndrome is essential for timely intervention and effective management. While they may share similar symptoms, each condition has distinct characteristics. A key difference in the symptoms comparison is speed: GBS symptoms escalate over days to weeks, while MS symptoms tend to flare and fade over months or years.
Symptoms of GBS
The most common and early signs of GBS are symmetric muscle weakness and tingling sensation in both legs. These sensations start from the feet and gradually move to the body’s upper part. In the worst case, it causes flaccid paralysis.
Other symptoms of GBS include:
- Decreased reflexes
- Shortness of breath
- Muscle pain or aching
- Coordination problems
- Difficulty walking or running
- Abnormal heart rate or blood pressure
- Difficulty with eye movement, facial movement, speaking, or swallowing
Symptoms of MS
Symptoms of MS typically include blurred or double vision, mobility problems, loss of balance, speech problems, cognitive and emotional disturbance, fatigue, bowel problems, depression, and sexual dysfunctions.
MS symptoms also tend to worsen temporarily when body temperature rises, for example, during exercise, hot weather, or a fever, a hallmark known as Uhthoff’s phenomenon that is not typical of GBS.
These symptoms typically become more aggressive over time if not caught early and treated. Without prompt care, individuals may face an increased risk of long-term complications affecting their overall quality of life and functional abilities.
How GBS and MS Are Diagnosed
Learning about the diagnostic differences between GBS and MS is vital for timely intervention. Accurate diagnosis often involves a combination of clinical evaluations and specialized tests tailored to each condition.
Diagnosis of GBS
Diagnosing GBS is primarily based on symptoms and a neurological examination. Healthcare providers may also employ the following diagnostic tests to confirm the condition:
- Lumbar Puncture (Spinal Tap): This test analyzes cerebrospinal fluid (CSF) for elevated protein levels with normal white blood cell count.
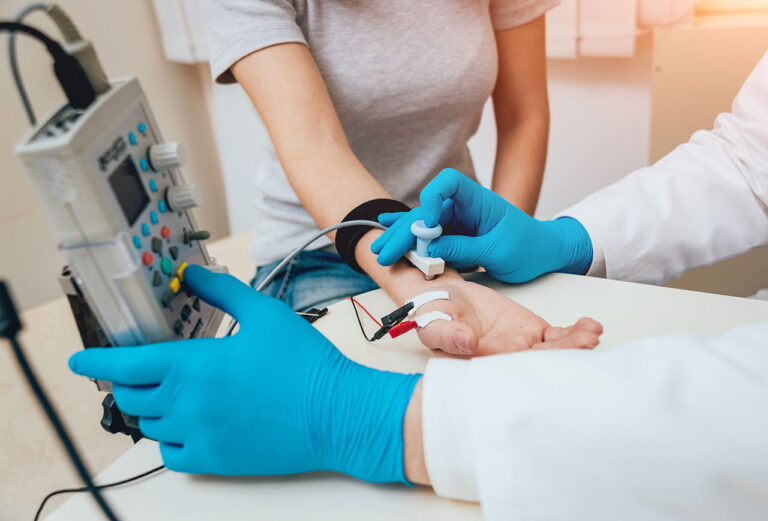
- Nerve Conduction Studies (NCS): This test measures how quickly electrical signals travel through the nerves, helping to identify nerve damage characteristic of GBS.
- Electromyography (EMG): This test assesses the electrical activity of muscles, revealing abnormalities in muscle response to nerve stimulation.
Diagnosis of MS
Diagnosing multiple sclerosis requires a comprehensive assessment that includes a detailed medical history and neurological examination. Various tests help to identify MS-specific changes in the central nervous system, such as:
- Magnetic Resonance Imaging (MRI): This imaging technique detects lesions in the brain and spinal cord, indicative of MS. MRI is one of the clearest ways to distinguish MS from GBS, since GBS does not usually produce brain or sp+inal cord lesions.
- Lumbar Puncture: Similar to GBS, CSF analysis can reveal oligoclonal bands, a sign of an inflammatory process in MS.
- Evoked Potentials (EPs): These tests measure the electrical activity in the brain in response to stimuli, helping to detect delays in nerve conduction.
Guillain-Barre Syndrome vs. Multiple Sclerosis: Treatment Options
There is no cure for multiple sclerosis and Guillain-Barre syndrome. However, there are treatment options that are used to manage the symptoms of each condition.
Treatments for GBS
Effective management of GBS involves a combination of treatment options tailored to the severity of the condition. These interventions aim to reduce symptoms and promote nerve healing.
The main treatment options for GBS include:
- High-Dose IVIG Treatment: IVIG therapy for GBS is used to help modulate the immune response. IVIG contains antibodies that can help block the damaging effects of the immune system on the nervous system.
- Plasma Exchange: Also known as plasmapheresis, this procedure involves the removal of plasma from the blood and replacing it with a substitute solution to help reduce the immune system’s attacks on the nervous system.
Treatments for MS
Multiple sclerosis requires a multifaceted approach aimed at managing symptoms while slowing disease progression. The treatment plan can vary depending on the type of MS and the individual’s specific symptoms.
The main treatment options for MS include:
- Steroid Medications: Corticosteroids, such as prednisone, reduce inflammation during MS relapses. These medications can help alleviate symptoms and promote recovery from acute episodes.
- Disease-Modifying Therapies (DMTs): These medications modify the course of the disease and reduce the frequency and severity of relapses. Examples of DMTs include interferon beta, glatiramer acetate, fingolimod, and dimethyl fumarate.
- Symptomatic Treatments: In addition to DMTs, various medications and therapies are available to manage specific symptoms of multiple sclerosis, such as muscle spasticity, fatigue, and bladder dysfunction.
Prognosis and Long-Term Outlook

Understanding the prognosis and long-term outlook for GBS and MS is crucial for patients and their families. Both conditions have distinct trajectories that can affect quality of life.
Prognosis for GBS
The prognosis for Guillain-Barre syndrome is generally favorable. A key difference between GBS and MS is that most patients with GBS experience significant improvements within weeks to months after treatment.
Up to 70% of individuals fully recover, although some may have lingering effects, such as weakness or sensory issues.
Prognosis for MS
In contrast, multiple sclerosis is a chronic condition with varying long-term outcomes. While some individuals may experience periods of remission, others may face progressive deterioration in function over time, requiring ongoing management and care.
Manage Multiple Sclerosis and Guillain-Barre Syndrome With AmeriPharma® Specialty Pharmacy
Understanding the differences between Guillain-Barre syndrome vs. multiple sclerosis can help you better manage these conditions. If you’re dealing with either MS or GBS and need specialty treatment, AmeriPharma® Specialty Pharmacy can help.
Our ACHC-accredited specialty pharmacy provides at-home IVIG infusions and hard-to-find medications for those with debilitating conditions in 40+ US states and territories.
Contact us today to speak to a specialist and receive the treatment you need with full-service coordination, copay assistance, and 24/7/365 support.
Frequently Asked Questions
Can Guillain-Barre be mistaken for MS?
Yes. Because GBS and MS both damage myelin and cause tingling, numbness, and muscle weakness, they can look alike early on. Doctors tell them apart by which nerves are involved (GBS affects peripheral nerves, MS affects the brain and spinal cord), how fast symptoms appear (rapid in GBS, episodic in MS), and test results: nerve conduction studies point to GBS, while MRI lesions point to MS.
What is mistaken for Guillain-Barre syndrome?
Several conditions can mimic GBS, including chronic inflammatory demyelinating polyneuropathy (CIDP), myasthenia gravis, transverse myelitis, spinal cord compression, tick paralysis, and, occasionally, multiple sclerosis. A neurological exam and tests such as a lumbar puncture and nerve conduction studies help confirm the diagnosis.
What virus causes Guillain-Barre syndrome?
No single virus causes GBS, but it often follows an infection. Common triggers include Campylobacter jejuni (a bacterium), cytomegalovirus, Epstein-Barr virus, Zika virus, influenza, and SARS-CoV-2 (COVID-19). The immune response to the infection is what ends up attacking the peripheral nerves.
Can you have both GBS and MS?
It is rare, but medical case reports describe people who have had both conditions. Having one does not usually cause the other, and the overlap appears to be uncommon rather than a typical progression.
Is Guillain-Barre or MS more serious?
They are serious in different ways. GBS is an acute illness that can be life-threatening in the short term if it weakens the breathing muscles, but most people recover well. MS is usually not immediately life-threatening, yet it is lifelong and can gradually cause disability. Outcomes depend heavily on early diagnosis and treatment for both.
Can Guillain-Barre syndrome turn into MS?
No. GBS does not turn into MS; they affect different parts of the nervous system. If GBS-like symptoms continue or keep returning for more than about eight weeks, the diagnosis may instead be CIDP, a chronic relative of GBS, rather than MS.